


Diabetic retinopathy remains one of the leading causes of vision loss among adults, yet vision-threatening diabetic retinal disease may develop even in patients who report no visual complaints and have little or no clinically apparent diabetic retinopathy.1-3 This case highlights the importance of careful comparison of serial retinal imaging and the value of optical coherence tomography (OCT) in identifying diabetic macular edema (DME) in the presence of an epiretinal membrane (ERM) that was not readily apparent during the clinical examination.
Case Report
A 77-year-old male presented for his annual comprehensive eye examination. His ocular history was significant for uncomplicated cataract surgery performed 3 years earlier. His medical history was notable for diabetes, hypertension, and hypercholesteremia, for which he was being medically managed. He had no previous history of diabetic retinopathy.
The patient reported no subjective change in his vision since his previous examination. Entering visual acuity was OD 20/50, OS 20/50-1. His best-corrected visual acuity (BCVA) measured OD 20/40 and OS 20/50. Examination of the anterior segment was unremarkable, with a well-positioned posterior chamber intraocular lens in each eye.
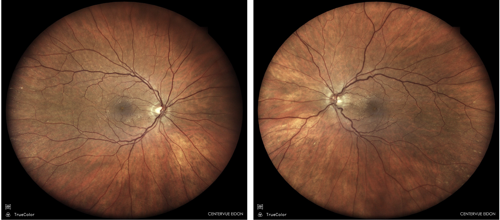
Widefield fundus photography using the iCare EIDON (iCare) imaging system revealed a subtle, irregular yellow lesion within the macular region. Closer inspection demonstrated a small, ring-like abnormality located within the macula. (Figure 1) Although the retinal findings appeared relatively subtle during the examination, comparison with fundus photographs obtained the previous year demonstrated a clear change in appearance. (Figures 2 and 3)
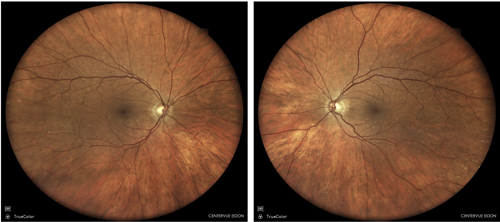
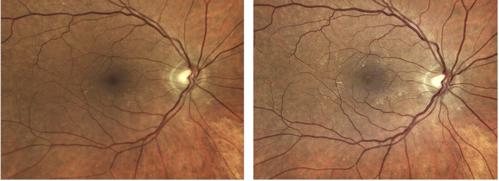
The unexplained reduction in BCVA and the newly identified retinal abnormalities warranted a spectral domain OCT imaging of the macula. OCT using the Optovue Solix (Visionix) demonstrated significant bilateral macular edema characterized by increased central retinal thickness (Figure 3) and multiple intraretinal cystic spaces extending through the central macula along with a mild epiretinal membrane. (Figure 4)
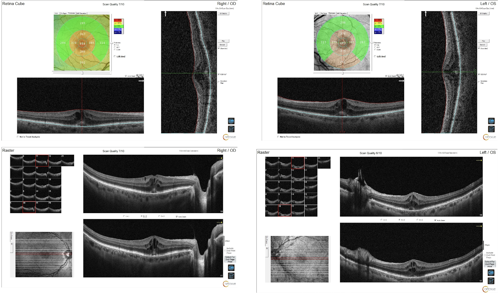
The patient was diagnosed with bilateral diabetic macular edema with an epiretinal membrane. This case illustrates that clinically significant DME may develop despite minimal symptoms and relatively subtle funduscopic findings, emphasizing the importance of multimodal retinal imaging in diabetic patients.
The examination findings and OCT images were reviewed with the patient in detail. Given the presence of clinically significant bilateral diabetic macular edema, an immediate referral was made to a retina specialist for further evaluation and management. The patient understood the findings and the importance of timely retinal intervention to preserve vision.
Discussion
This case demonstrates several important clinical lessons. Patients with diabetes may develop visually significant DME while remaining largely asymptomatic. Small changes on fundus photography may represent significant underlying retinal pathology. Comparing current retinal images with previous photographs can reveal subtle progression that may otherwise be overlooked.
The OCT remains the gold standard for confirming the presence, location, and severity of DME and should be obtained whenever retinal abnormalities or unexplained reductions in visual acuity are identified. Early detection and prompt referral to a retina specialist are critical to preserving long-term visual function. This case demonstrates this important concept.
References
1. Wong TY, Sun J, Kawasaki R, et al. Guidelines on diabetic eye care: the International Council of Ophthalmology recommendations for screening, follow-up, referral, and treatment based on resource settings. Ophthalmology. 2018;125(10):1608-1622.
2. Browning DJ, Stewart MW, Lee C. Diabetic macular edema: evidence-based management. Indian J Ophthalmol. 2018;66(12):1736-1750.
3. Schmidt-Erfurth U, Garcia-Arumi J, Bandello F, et al. Guidelines for the management of diabetic macular edema by the European Society of Retina Specialists (EURETINA). Ophthalmologica. 2017;237(4):185-222.

Content sponsored by
iCare / Visionix